Best Anabolic Steroids

Press Enter to search the full catalog.

US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
Back to all products
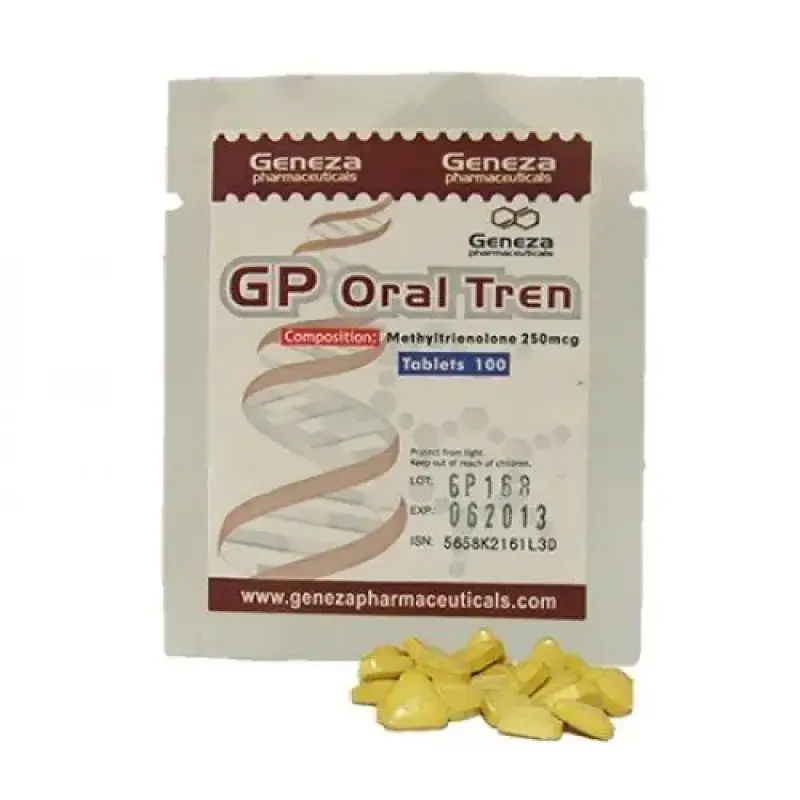
GP Oral Tren Methyltrienolone - Geneza Pharmaceuticals

Geneza Pharmaceuticals

GP Oral Tren Methyltrienolone - Geneza Pharmaceuticals

Oral · 250 mcg/tab · 100 tabs

Out of stock
CompoundMethyltrienolone
ClassDHT-derived oral
Half-lifeNot confirmed
DetectionNo confirmed window
Liver toxicityHigh
Water retentionNone
One box of 100 tablets at 250 micrograms each, which is why the numbers on this page are written in micrograms rather than milligrams. The molecule is a methylated trenbolone with a 19-nor backbone, so it behaves nothing like the injectable acetates on the neighbouring cards: it arrives within days, acts for hours only, and is counted among the most punishing orals for the liver. The exact half-life and the urinary detection window are not established in the sources, and the compound is banned in sport at all times.
GP Oral Tren Methyltrienolone - Geneza Pharmaceuticals
Order Now, Ships Today
$90.00
Quality First

All products are manufactured under strict quality standards and independently tested before release. By purchasing, the buyer agrees to use these products in compliance with all applicable laws.

Product Overview

Best Anabolic Steroids lists GP Oral Tren from Geneza Pharmaceuticals: 100 tablets of methyltrienolone at 250 micrograms each. The dose on the label is the first unusual thing about the product, because the whole daily intake of this molecule is measured in a fraction of a milligram, and a single box at that strength can outlast several cycles of a normal oral.

Methyltrienolone is trenbolone with a methyl group added at the seventeenth carbon so that the compound survives the digestive tract. That one change produces a substance that is far more androgenic than the injectable trenbolone esters, and far less forgiving on the liver. The backbone is 19-nor, the same family as trenbolone and nandrolone, so it does not convert into estrogen. What it does carry is progestogenic activity, which is why chest issues can appear on this tablet without any aromatization taking place at all.

The injectable GP Trenbolone range and this tablet are often discussed as if they were the same drug at different prices. They are not. An acetate or an enanthate builds up and leaves slowly and is managed in weeks; methyltrienolone appears almost immediately, clears within hours of the tablet, and is managed in days. Both shut down natural production, and both are hard on the cardiovascular system, but only one of them can be stopped mid-week with the confidence that the level is already falling.

Dosage Protocol

Every figure below is a reference point from the sources rather than a clinical prescription, and the bands are deliberately narrow: the gap between a productive amount and a harmful one is small on this compound.

Beginner 250 mcg each day for two weeks, and two weeks is a complete block at this level
Intermediate 250-500 mcg each day for two to three weeks, divided through the day
Advanced Up to 500 mcg each day, rarely more, and never past three to four weeks
Female Not recommended; androgenic load and hepatic risk are both extreme, and no female protocol is published
Administration Oral, split into several small takes; liver support alongside; enzymes checked inside the block

Splitting the daily amount matters more here than on a long-ester product, because the sources describe an effect that lasts only hours and a half-life they never manage to put a number on. Without a confirmed figure, timing is built from practice: small amounts spread across the day rather than one dose in the morning. The total daily amount is what the sources discuss, not the size of a single tablet.

A rule that does not bend: this tablet never runs beside another alkylated oral. The hepatic load of two such compounds is additive, the fact base states it plainly, and there is no amount of liver support that makes the pairing sensible.

Suggested Protocols

This is a niche product used as a short addition to an existing injectable stack, never as its own cycle.

Strength peak
Two weeks added to the middle of an ester block, then stopped; the injections continue while the tablet comes out
Density in a deficit
Three dry compounds in one block; the two DHT products handle appearance while the tablet supplies the strength, and blood pressure is followed weekly
What not to do
GP Oral Tren + GP Superdrol + GP Oxan
Two or three alkylated orals in the same week is the arrangement the sources warn about; this row is listed so it can be avoided

What to Expect

  • Strength jumps within days. Users describe a sharp rise in the first few days, faster than any ester can deliver, with wellbeing going the other way at the same time.
  • Hardness without size. Density and a tighter look show in the first week or two, and scale weight hardly moves because nothing here converts to estrogen.
  • Appetite and mood dip. Losing interest in food and feeling generally unwell are described as early signs that the body is not tolerating the compound.
  • Enzymes move quickly. The liver panel can be the first marker to shift, which is why the block is measured in days rather than months.
  • Chest sensitivity is possible without estrogen. Progestogenic activity explains it, and a dopamine agonist is the usual answer if it appears.
  • Sleep and temper change. Insomnia and short temper are common complaints and are tied to the dose.

Side Effects and Management

The liver leads the list, and the reported pattern is a fast rise rather than a slow drift, which is why this compound is treated as one of the most aggressive orals in circulation.

Hepatic injury and enzyme spikesShortest possible block, TUDCA and NAC alongside, enzymes mid-block; the rise can be rapid. High risk, dose-dependent.
Malaise, weakness, no appetiteStop the tablet rather than lowering it; this is the signal users report first. Common even at low amounts.
Progestogenic chest discomfortMonitor and treat with a dopamine agonist where appropriate; it happens without any aromatization. Dose-related.
Lipid shiftHDL falls and LDL rises while the block runs; a lipid panel before and after is the practical response. Dose-dependent.
Irritability and insomniaReduce the amount or close the block; the trenbolone character of the molecule shows here. Often reported.
Complete shutdown of the axisExpect it, and plan therapy before the first tablet; recovery is dealt with in the next section. Expected at any effective amount.

Post-Cycle Therapy

Because no depot is left in the tissue, therapy can begin almost immediately, and the sources put the start about one or two days after the final tablet. Even a two-week block at this strength is long enough to switch the axis off, and a low amount does not excuse a partial recovery plan.
StartOne to two days after the last tablet, once the liver panel has been read and is stable
Option AGP Nolvadex, 40 mg a day for the opening seven days and 20 mg a day afterwards, about four weeks
Option BGP Clomiphene at 50 mg a day taken in the morning, four weeks
Not a PCT drugAn aromatase inhibitor such as GP Exemestane has no place in restarting the axis and cannot substitute for a SERM
RecheckTestosterone, LH, FSH and estradiol roughly a month after therapy closes, together with liver enzymes and lipids
Where it fitsMethyltrienolone has no record as a fertility or hypogonadism treatment and is never the answer to a stalled restart
This material is published for educational and research reference purposes only. The compounds described are research-grade materials supplied for laboratory work and are not presented here as medicines or as a treatment for any condition. Dosing information reflects published clinical and reference data for the active substances, not a recommendation or a prescription. The liver injury associated with this molecule is documented and is cited here as part of its record. Nothing on this page should be read as medical advice. Keep all products out of reach of children and follow the regulations that apply in your country.
What is methyltrienolone and what is this tablet?
GP Oral Tren is a box of 100 tablets of methyltrienolone at 250 micrograms each, sold by Geneza Pharmaceuticals. The molecule is trenbolone with a methyl group at the seventeenth position, which lets it pass through the stomach intact, and it is also known as metribolone or R1881. It belongs to the 19-nor family and does not convert to estrogen.
How much oral tren do people take?
The reference amounts are tiny because the compound is so strong: 250 micrograms a day at the low end, 250-500 micrograms a day in the middle, and 500 micrograms a day as a rarely used ceiling. The daily figure is divided into several small takes across the day rather than swallowed at once.
How long can a methyltrienolone block last?
Two weeks at the starting amount, two to three weeks in the middle of the range, and three to four weeks as an absolute ceiling. Very few reports describe going beyond a month, and none of them describe a benefit that justifies it. The limit is the liver rather than tolerance.
Is oral tren as strong as injectable trenbolone?
The sources describe methyltrienolone as considerably more potent per milligram than the injectable esters, and far harsher on the liver. The practical difference is timing: an injectable builds a level over weeks and leaves it behind, while this tablet works while it is in the bloodstream and is gone from the body within hours of the last dose.
Why does oral tren stress the liver so heavily?
The methylation that lets the tablet survive digestion also makes the liver process a molecule it handles poorly, and animal data class methyltrienolone among the most hepatotoxic anabolic steroids studied. Reports describe enzymes climbing fast, so a mid-block panel and a short block are not optional extras.
Does it cause gynecomastia if it does not aromatize?
Estrogen is not the mechanism, but chest discomfort is still described. The molecule has progestogenic activity, which can produce symptoms without any conversion to estradiol, and an aromatase inhibitor will not address it. Where it appears, the sources point to a dopamine agonist and to stopping the compound.
Is methyltrienolone detectable in a drug test?
Yes, and the compound sits in WADA class S1, prohibited at all times rather than only in competition. No specific urinary detection window is stated in the sources, so anyone subject to testing has no reliable figure to plan around, and should treat the substance as detectable.
Do you need PCT after a short oral tren block?
Yes, even after two weeks. Natural production is suppressed at these amounts, and because nothing is stored in the tissue there is no ester to carry the level while the axis resumes. A SERM for about a month, starting one or two days after the final tablet once the liver panel looks stable, is the shape the sources describe.

No reviews yet

Be the first to share your experience with GP Oral Tren Methyltrienolone - Geneza Pharmaceuticals

Log in to write a review

Complete the protocol

Stack it with

View all →
Added to cart
