Best Anabolic Steroids

Press Enter to search the full catalog.

US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
Back to all products
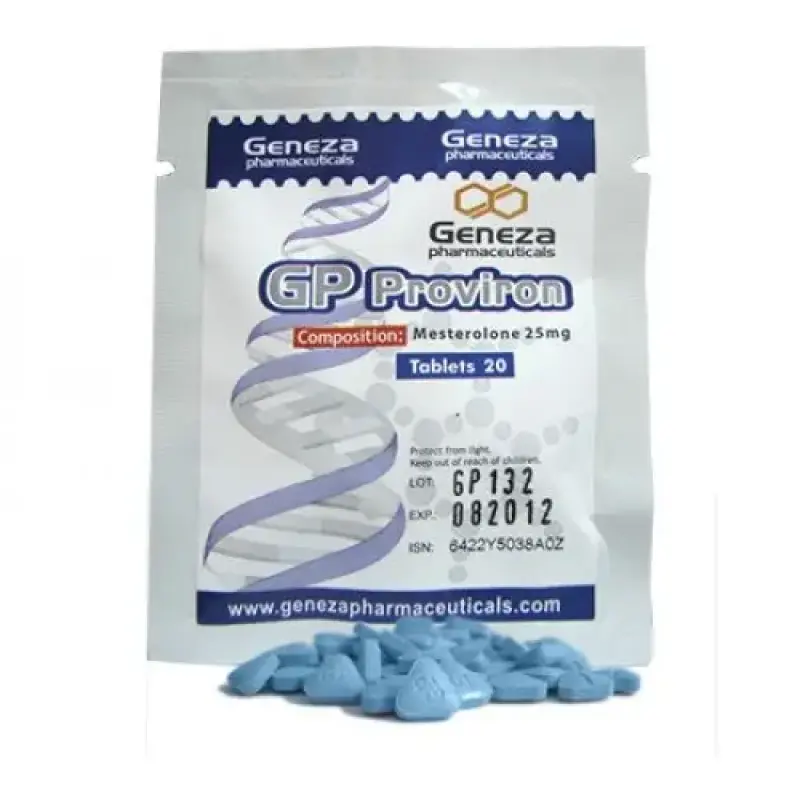
GP Proviron Mesterolone 25 mg - Geneza Pharmaceuticals

Geneza Pharmaceuticals

GP Proviron Mesterolone 25 mg - Geneza Pharmaceuticals

Oral · 25 mg/tab · 20 tabs

Out of stock
CompoundMesterolone
ClassDHT-derived oral androgen
Half-life12-13 hours
Detection10-14 days or more
Liver toxicityLow
Water retentionNone
Twenty tablets of mesterolone at 25 mg, a dihydrotestosterone-derived oral androgen with strong androgenic and weak anabolic activity. It is one of the few orally active anabolic steroids that is not alkylated at the seventeenth carbon, which is why its hepatic risk is described as low rather than high. Its main action in a stack is on sex hormone binding globulin: by occupying that carrier protein it leaves more testosterone unbound and available, and it never converts to estrogen.
GP Proviron Mesterolone 25 mg - Geneza Pharmaceuticals
Order Now, Ships Today
$37.00
Quality First

All products are manufactured under strict quality standards and independently tested before release. By purchasing, the buyer agrees to use these products in compliance with all applicable laws.

Product Overview

Best Anabolic Steroids lists GP Proviron from Geneza Pharmaceuticals: 20 tablets of mesterolone at 25 mg, the oral androgen that pharmacy shelves have sold for decades under the name Proviron. It is a dihydrotestosterone derivative, which places it in the same structural family as stanozolol and drostanolone, and its character is androgenic rather than anabolic. Muscle does not come from this tablet.

Two features make it unusual among oral steroids. The first is that the molecule carries no alkyl group at the seventeenth carbon. That group exists in most oral anabolics to survive the digestive tract, and it is the reason those products load the liver; mesterolone is absorbed without it, and the reference material accordingly describes hepatic risk as low. The second is its hold on sex hormone binding globulin. Most of the testosterone in circulation is carried by that protein and cannot act while it is held, so a compound that occupies the binding sites raises the fraction that is free. Users describe that as more of what they already had rather than as a new effect of its own.

Because it does not aromatize, there is no fluid to shed and no breast tissue risk from this tablet. The flip side of a pure DHT compound is that anything sensitive to androgens feels it sooner: the scalp, the skin and the vocal cords are the places to watch, which is why the female answer in the sources is a flat refusal rather than a small dose.

Dosage Protocol

The figures come from reference material and from the replacement-therapy schedule the drug was designed around, not from a prescription written for a bodybuilder. In clinical use mesterolone is given at 25 mg two or three times a day; sports use sits lower and shorter.

Beginner 25 mg a day, taken for as long as the cycle it supports, split into two takes because of the twelve hour half-life
Intermediate 50 mg a day in two doses, which is where most stack use sits
Advanced 50-100 mg a day; nothing above that appears in the sources and nothing suggests a reason to try
Female Not recommended at all: the androgenic pressure on voice and hair is considered too high to manage by lowering the amount
Administration By mouth, divided through the day, usually with food if the stomach is easily upset

Placement matters more than the number. This product is added to a stack rather than run as one, and its value is highest where the cycle contains an aromatizing compound, because the freed testosterone comes from the circulating pool the cycle has created. A course built only from mesterolone would leave the user androgenised on paper and unchanged in the mirror.

It is also not a recovery drug and not a substitute for a base. Anyone whose natural production has stopped needs hormone replacement or a proper post-cycle protocol, and neither of those is what this tablet does.

Suggested Protocols

Three placements cover the way it is normally used, and the fourth row describes what it cannot be.

Androgenic floor
Added to an ester block to free up testosterone and hold libido steady; the injections remain the part that builds tissue
Cutting with a dry oral
GP Masteron - 300 mg weekly + GP Stan 50 Inj - on alternate days + GP Proviron - 25-50 mg a day
All three are DHT-based and none of them holds water; the tablet is the smallest part of the load and adds no hepatic burden of its own
Estrogen control done properly
GP Anastrozole + GP Exemestane + GP Proviron - different mechanism
The two inhibitors lower estradiol; mesterolone never touches it, so it is not an alternative to either of them
Recovery
Restarting the axis is SERM work; this tablet suppresses production slightly rather than restoring it

What to Expect

  • Libido comes up early. Most reports put the change inside the first week or two, and it is the effect users notice first.
  • A denser appearance, not new size. The look tightens while the scale stays where it was, since nothing here holds fluid or adds contractile tissue.
  • Free testosterone can rise. Occupying binding globulin leaves a larger unbound fraction of whatever testosterone the cycle provides.
  • No fluid, no chest swelling. The molecule cannot be converted into estrogen, so neither of those problems originates here.
  • Androgenic signals show up quickly. Oily skin, new acne and hairline shedding are the usual early complaints.
  • Production is suppressed modestly. The tablet is not neutral on the axis, even though it is mild compared with a full cycle of injectables.

Side Effects and Management

The list is dominated by androgenic effects, and the management is mostly dose discipline. Nothing here is described as a hepatic concern.

Acne, oily skin, hair sheddingSkin care and a smaller amount; the DHT origin of the molecule explains all three. Common and dose-related.
Voice change in womenThe sources advise against female use altogether rather than offering a low dose; virilization is the stated reason.
High libidoOften the wanted effect and occasionally an unwanted one; it settles when the amount is reduced.
Lower HDLA lipid panel before and after the block; oral androgens of any kind tend to move this number. Dose-related.
Mild suppression of the axisKeep a testosterone base in the stack and handle recovery according to the cycle, not according to this tablet.
Stomach irritationTake the tablet with food; the complaint is minor and easily managed.

Post-Cycle Therapy

Mesterolone is not a therapy product and does not require a therapy of its own. It sits inside a cycle, it ends with that cycle, and the recovery plan belongs to whatever injectables were running underneath. Because the tablet itself clears within a day or so of stopping, it never delays the start of a SERM course the way a long ester does.


RoleA support compound inside the cycle, withdrawn on the same day the other orals stop
Option AGP Nolvadex at 40 mg a day, halving after the opening week, over roughly four weeks
Option BGP Clomiphene at 50 mg each morning across four weeks
TimingSet by the longest ester in the cycle, not by this tablet; waiting is decided on the injection, not on the pill
Follow-upA hormone panel covering testosterone, LH and FSH, plus estradiol and cholesterol, once therapy has finished
This material is published for educational and research reference purposes only. The compounds described are research-grade materials supplied for laboratory work and are not presented here as medicines or as a treatment for any condition. Dosing information reflects published clinical and reference data for the active substances, not a recommendation or a prescription. Nothing on this page should be read as medical advice. Keep all products out of reach of children and follow the regulations that apply in your country.
What is GP Proviron used for?
Mesterolone is an oral androgen with strong androgenic and weak anabolic activity. Inside a stack it is used to free up testosterone by occupying sex hormone binding globulin, and users report a firmer look and higher libido. It is not used to add muscle mass, and in bodybuilding it almost never appears alone.
Does mesterolone really raise testosterone?
Not the total figure, but the free fraction. Testosterone spends most of its time bound to a carrier protein and unable to act; mesterolone occupies those binding sites, so more of the existing hormone circulates unbound. That is why the tablet is described as making a cycle more effective rather than as producing testosterone.
How much Proviron is taken?
Clinical replacement dosing is 25 mg two or three times a day, while sports use typically runs 25 mg a day at the low end and 50 mg a day in the middle, with 50-100 mg a day as the outer band in the sources. Because the half-life is around twelve hours, a daily amount is usually divided into two takes.
Is Proviron liver toxic?
It is treated as one of the least troublesome oral steroids for the liver, because the molecule is not alkylated at the seventeenth carbon and passes through without the modification that makes most oral anabolics hard on that organ. Its hepatic risk is described as low rather than absent, and it is still an oral androgen taken daily.
Can women use Proviron?
The sources say no rather than yes with caution. Acne, hair loss and voice change are listed as the expected androgenic effects, and lowering the amount is not presented as a way to make them safe. Women looking for a mild oral are pointed towards oxandrolone instead, which carries a documented low-dose female schedule.
Does it cause water retention or gynecomastia?
Neither originates from this tablet, because a DHT-derived androgen has no route to estrogen. Any fluid or chest issue in a stack comes from the aromatizing injectables beside it, and the response is to test estradiol and act on that number. Adding an inhibitor in the hope of fixing a mesterolone problem would be aimed at the wrong target.
Can Proviron replace a testosterone base?
No. It does not supply testosterone, it does not restore production after a course and it cannot carry a cycle on its own. Its anabolic activity is described as weak, which means a stack built around it would suppress the user while building very little. The ester underneath remains the base.
How long does mesterolone stay in the body?
The half-life is around twelve to thirteen hours, so the tablet is gone from the blood fairly quickly, but metabolites remain detectable in urine for roughly ten to fourteen days and sometimes longer depending on the amount and how long it was run. Anyone subject to testing should treat the longer figure as the working assumption.

No reviews yet

Be the first to share your experience with GP Proviron Mesterolone 25 mg - Geneza Pharmaceuticals

Log in to write a review

Complete the protocol

Stack it with

View all →
Added to cart
