Best Anabolic Steroids

Press Enter to search the full catalog.

US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
US Domestic discreet shipping
Third-party batch tested
HPLC & MS verified purity
Trusted Anabolic Manufacturers Only
Back to all products
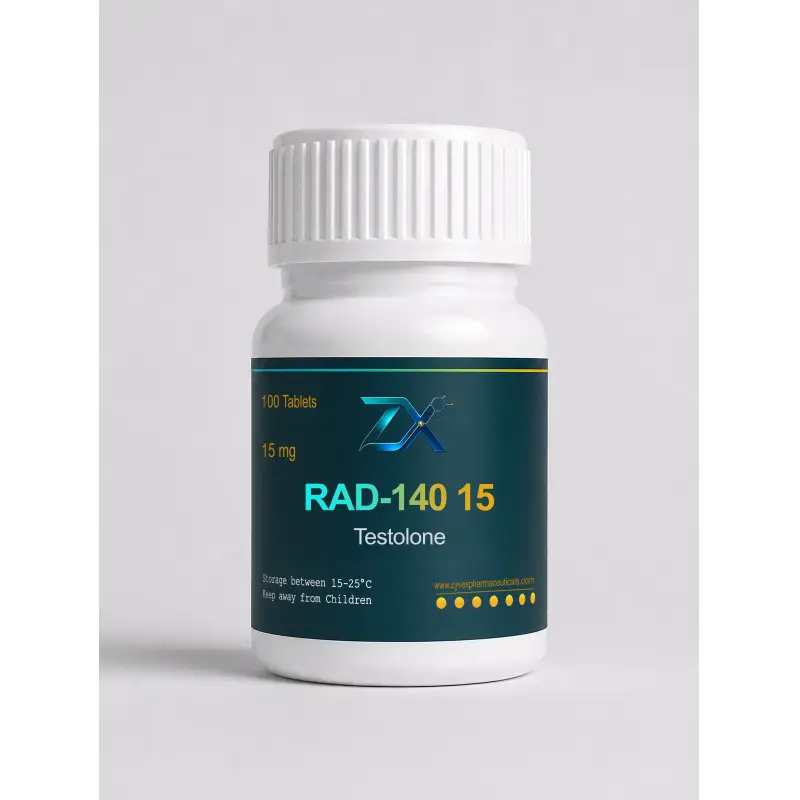
Testolone RAD 140 Tablets - Zyvex Pharmaceuticals

Zyvex Pharmaceuticals

Testolone RAD 140 Tablets - Zyvex Pharmaceuticals

Oral · 15 mg/tab · 100 tabs

Out of stock
CompoundTestolone RAD 140
ClassSARM
Half-life45-60 hours
DetectionProhibited class
Liver toxicityModerate
Water retentionNone
A hundred tablets of a non-steroidal androgen receptor agonist with one of the longest half-lives in its class, which is why it is taken once a day rather than twice. It does not aromatise, so there is no fluid or breast tissue effect. The trial record is thin and unpleasant in places: enzyme rises in preliminary work, a fall in testosterone in animal studies, and PSA and SHBG shifts. Development for muscle-wasting conditions has been abandoned, and nothing about the compound is approved for human use.
Testolone RAD 140 Tablets - Zyvex Pharmaceuticals
Order Now, Ships Today
Quality First

All products are manufactured under strict quality standards and independently tested before release. By purchasing, the buyer agrees to use these products in compliance with all applicable laws.

Product Overview

Zyvex Pharmaceuticals offers Testolone as one hundred tablets, and the compound behind the name is RAD 140, also written vosilasarm. It is a non-steroidal agonist at the androgen receptor with a high affinity for that target, which is the reason a small oral amount produces a measurable androgenic signal at all. The long half-life of 45 to 60 hours makes the once-daily tablet arithmetic simple and keeps the level steady between doses.

What the compound is not is a steroid, and the practical differences are easy to list. It does not aromatise, so fluid retention and breast tissue effects do not belong to it and an aromatase inhibitor has no role. It does suppress natural testosterone, which was shown directly in primate work where the fall reached roughly half of baseline. And it carries a liver signal that is unusual for something without the methyl group of an oral steroid: preliminary clinical work reported rises in both AST and ALT, and the literature on non-medical use describes cases of liver injury.

The development history is worth knowing before the numbers. The compound was studied for breast cancer and later considered for muscle-wasting conditions, and those programmes were stopped. That leaves the consumer with a research compound whose human dataset is small and whose selling amounts sit well above the amounts anyone studied. It is filed with the other oral products in the range, from Ligandrol LGD 4033 through to Ostarine MK 2866, and it is the most potent of the three on paper.

Dosage Protocol

No approved dose exists for any indication. The rows below separate research convention from the higher amounts used outside it.

Level Amount Length Note
Beginner 5-10 mg daily 8-10 weeks Research convention rather than a labelled figure
Intermediate 10-20 mg daily 8-12 weeks The band used most often; one dose a day is enough
Advanced Up to 30 mg daily 8-12 weeks Above the clinical reference points, with side effects rising accordingly
Female Not confirmed - Virilisation risk with no safe protocol in the sources
Route Oral tablet Once daily Long half-life holds the level; liver enzymes, lipids and testosterone belong on the schedule

For contrast, the breast cancer research used 50 to 150 mg a day with a maximum tolerated dose of 100 mg a day, which is an oncology context and is quoted here only to show how far the consumer range sits from an approved setting. Nobody has published a safety dataset for 10 to 30 mg a day in healthy men.

Suggested Protocols

These are catalogue arrangements rather than tested stacks, and the compound is the receptor arm in every one of them.

Strength block with a hormone layer
Eight to twelve weeks, with liver enzymes and testosterone read inside the block rather than after it
Recovery once the receptor signal stops
Starts three to seven days after the final tablet, and lasts until the blood work says the axis is back
SARM against oral steroid
Testolone - receptor route without aromatisation + Anavar Oxandrolone - the alkylated oral beside it
The comparison users make most often, and the reason to think about the liver: one compound is methylated, the other is not, and both can move enzymes

What to Expect

  • Users describe the first noticeable change around weeks two and three, which is a community timeline rather than a formal finding.
  • Strength and size move gradually when training and calories are already in place, and the change is smaller than a steroid cycle produces.
  • The 45 to 60 hour half-life means one tablet a day holds a flat level, so splitting the amount across the day adds nothing.
  • Testosterone falls: primate work showed a suppression of around fifty percent, and that is what lies behind late-course fatigue and low interest.
  • Lipids shift in models, with changes in triglycerides, LDL and HDL, so a panel belongs in the plan.
  • Liver enzymes and PSA rose in early clinical work, and prostate-specific antigen plus SHBG are worth reading for anyone monitoring closely.

Side Effects and Management

Rising AST and ALTPreliminary data reported a rise in a large share of subjects; check enzymes during the course and stop on a significant change.
Suppressed testosteroneAround a fifty percent fall in animal work; a testosterone reading mid-course and a recovery step afterwards.
Lipid movementTriglycerides, LDL and HDL all moved in models; diet, cardio and a panel on the schedule.
Nausea, constipation, appetite lossRecorded in early trials; hydration and nutrition first, and stop if it does not settle.
Rising PSA and falling SHBGReported in preliminary data; these are markers a clinician can interpret in context.
Serious events in the fieldLiver toxicity and a case of myocarditis have been described in the non-medical literature; any chest pain, breathlessness or jaundice means urgent care.

Post-Cycle Therapy

The recovery question is not whether this compound suppresses the axis, because it does, but how quickly the signal fades. With a half-life of 45 to 60 hours the tablet is largely gone in a week, so the recovery window opens sooner than after a long injectable ester and later than after a SARM with a shorter tail.


OnsetThree to seven days after the last dose as a practice guide, not an approved schedule
Option ATamoxifen at 40 mg daily for two weeks, then 20 mg daily for two more
Option BClomid Clomiphene at 50 mg daily for three to four weeks
Light coursesEven small amounts can lower the axis, so the recovery step is judged on a reading rather than on the size of the course
Follow-upTotal testosterone with LH and FSH, liver enzymes and a lipid panel, taken four to six weeks after the recovery stage ends
This page is published for educational and research reference purposes only. Testolone has no approved medical use in any country, and the material described here is supplied for laboratory reference rather than as a treatment for any condition. Dosing information reflects research convention and published trial values, not a recommendation or a prescription. Nothing on this page is medical advice, and the legal status of this class varies between jurisdictions. Keep all products out of the reach of children.
What is Testolone from Zyvex?
One hundred tablets of RAD 140, a non-steroidal agonist at the androgen receptor with a high affinity for that target and a half-life of 45 to 60 hours. It is an investigational compound with no approved use, and the programmes that once studied it for muscle-wasting conditions were discontinued.
How does it work and how often is it taken?
It binds the androgen receptor and switches on the genes that receptor governs, without a steroid skeleton and without being converted to estrogen. Because clearance takes close to two days, the level stays flat on a single daily tablet. That long tail is also why the compound keeps working for a day or two after the course stops, which is unusual in this class.
What amounts are used?
Outside research the range runs from 5 to 30 mg a day for eight to twelve weeks, with 10 to 20 mg being the usual band. Clinical work in breast cancer used 50 to 150 mg a day, but that is an oncology setting with a different risk balance and it is not a template for a physique plan. No dose is approved for anything.
Does it need a recovery step afterwards?
Yes. Primate work showed testosterone falling by about half, so the axis is genuinely suppressed. Because the tablet clears within roughly a week, a SERM such as Nolvadex Tamoxifen can start three to seven days after the last dose and run for weeks, with the result confirmed by a blood test rather than by how training feels.
What did the trials show about safety?
Enzyme changes stand out: AST and ALT rose in a large share of subjects in preliminary work, PSA and SHBG moved as well, and lipid parameters shifted in models. Nausea, constipation, dehydration and appetite loss were also recorded. The literature on non-medical use adds cases of liver injury and one report of myocarditis, which is why a panel and an exit plan matter here.
Is it a controlled substance in sport?
The class is prohibited, so detection in urine is possible and a tested athlete cannot use it. The primary sources do not publish a precise detection window for this particular compound, which is exactly why guessing about timing is a poor strategy. Where a product can be found in urine at all, a ban applies whenever it is found.
How does it compare with the other SARMs here?
It is the most potent of the oral three on paper and the least comfortable on paper as well, between the liver signal and the testosterone fall. Ostarine is milder and better studied, while Ligandrol sits between them. None of the three is approved, and all three suppress the axis to some degree.
Can it be combined with an oral steroid?
It can be, but the risk stack is the reason to hesitate. This compound already raises liver enzymes without methylation, and the oral steroid beside it, such as Anavar Oxandrolone, adds the methylated load. Two liver-active compounds in one course means a shorter block and more frequent panels, not a stronger block.

No reviews yet

Be the first to share your experience with Testolone RAD 140 Tablets - Zyvex Pharmaceuticals

Log in to write a review

Complete the protocol

Stack it with

View all →
Added to cart
