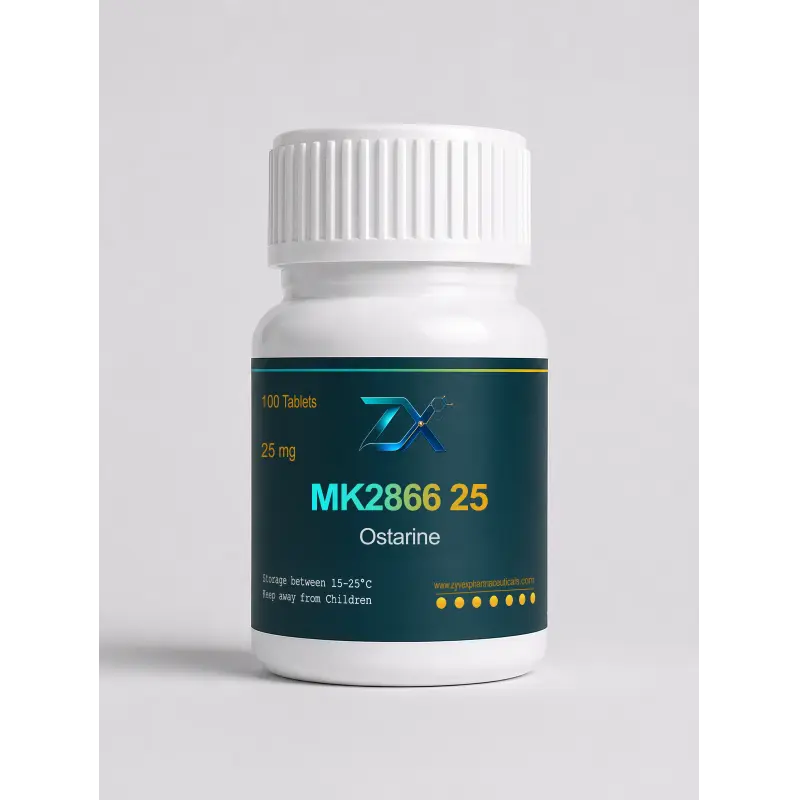
Product Overview
Zyvex Pharmaceuticals packs Ostarine as one hundred tablets carrying the code MK 2866, and the compound is enobosarm, the selective androgen receptor modulator with the deepest research file in the class. Across roughly twenty-five clinical studies and more than seventeen hundred participants, doses from 1 to 100 mg a day were examined, which is a far wider dataset than any of its neighbours can claim.
The tablets sold here are oral, non-steroidal and non-aromatising, so fluid retention and breast tissue side effects do not belong to this molecule and an aromatase inhibitor has nothing to act on. Two other findings do belong to it. Natural testosterone fell in a dose-dependent way, with a drop of about thirty-one percent at 1 mg a day and about fifty-seven percent at 3 mg a day in healthy older men. And HDL fell while LDL did not move in the same work, which is the pattern behind the lipid warning.
Its reputation as the mildest oral in the range comes from those numbers, and it is a fair description. It is not a description of a harmless product. A modest androgenic signal is still a signal, the axis answers it by slowing production, and the exit from a course still needs to be planned. For a stronger receptor effect with more risk attached, the Testolone RAD 140 card sits beside this one; for a comparison with a methylated oral, see Anavar Oxandrolone.
Dosage Protocol
Nothing below is an approved dose. The table shows the research span and the amounts used outside it.
| Level | Daily amount | Duration | Comment |
| Beginner | 10 mg daily | 8 weeks | Below the usual community figure, with testosterone and enzymes monitored |
| Intermediate | 10-25 mg daily | 8-12 weeks | The common band; one dose a day is enough |
| Advanced | 25-30 mg daily | 8-12 weeks | Top of the range, with masculinising effects in women almost unstudied at any amount |
| Female | Not confirmed | - | No safe protocol appears in the sources |
| Route | Oral tablet | Once daily | Half-life of 14 to 24 hours; most exits in faeces, with roughly a fifth to a quarter in urine |
Published work ran as high as 100 mg a day in some settings and as low as 1 mg a day in others, so the range in the literature is enormous. What matters for the person holding the box is that the conservative findings came from 1 to 3 mg a day, and the community amounts sit many times above that.
Suggested Protocols
The arrangements below are catalogue suggestions rather than tested stacks. In each one the compound supplies the receptor signal and the other products cover a different problem.
What to Expect
- The first two to four weeks bring a gradual change in condition, with lean tissue holding up better than it otherwise would in a deficit.
- Testosterone falls as the amount rises, so the drop at 1 mg a day is roughly a third and the drop at 3 mg a day is closer to half.
- HDL decreases in the research while LDL holds steady, which is a worse lipid picture rather than a mixed one.
- Liver enzymes rise in studies, so the tablet is not liver-neutral even though it is not a methylated steroid.
- Users often report sore joints easing, and that claim comes from community experience rather than from any published trial.
- The tablet is an investigational compound with no approval, and the safety data were gathered at amounts below the ones sold.
Side Effects and Management
Post-Cycle Therapy
Suppression here is smaller than with a strong injectable, and it is still real enough to need handling. The tablet clears in three to five days at this half-life, so the recovery stage begins sooner than after a long ester, and the starting point is the same pair used across the class.


