Sep 22, 2026 · 11 min read
Post-Cycle Therapy (PCT): What It Is and How It Works
BestAnabolicSteroids.com
Independent research & quality review desk
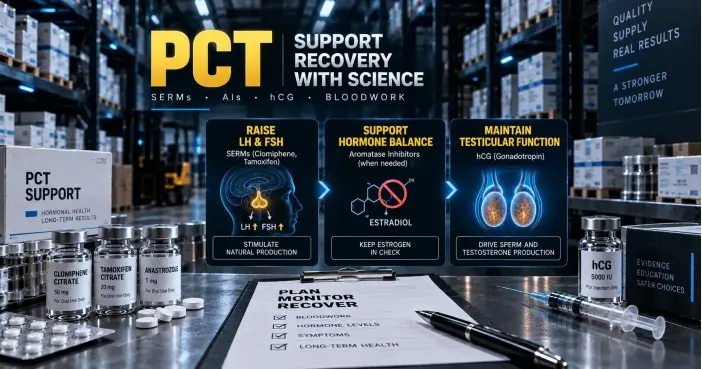
Post-cycle therapy, usually shortened to PCT, is the period after a course of suppressive compounds when the goal is to bring the body's own testosterone production back online. In clinical practice this is done with prescription medicines, most often SERMs such as clomiphene or tamoxifen, and progress is measured with bloodwork rather than with how you feel.
What PCT Actually Refers To
The term covers medicines that act on the pituitary to raise LH and FSH, the two signals that tell the testes to produce testosterone. Clomiphene citrate works as an estrogen antagonist at the level of the pituitary gland and stimulates the release of LH and FSH, which in turn drives both the steroidogenic and spermatogenic functions of the testes (Rambhatla et al., Reviews in Urology, 2016).
Two details matter when you read protocols online. First, clomiphene is not one substance but two isomers, zuclomiphene and enclomiphene, and the same source notes this when comparing preparations. Second, in men this use sits outside the approved indication: using clomiphene to restart endogenous testosterone production is off-label, and the first study to test the feasibility of exactly that approach in men with anabolic steroid-induced hypogonadism was published only in 2024 (Havnes et al., 2024).
What a PCT Protocol Actually Contains
Strip away the branding and most published protocols are combinations of three things. The table below shows what each class does and where it appears in the literature, so you can tell which parts of a protocol are supported by data and which are convention.
| Class | What it does | Where it appears |
|---|---|---|
| SERMs (clomiphene, tamoxifen) | Block estrogen feedback at the pituitary, which raises LH and FSH | The main subject of the clinical reviews on male hypogonadism |
| Aromatase inhibitors | Lower estradiol conversion, used when the testosterone to estradiol ratio is the problem | Studied alongside SERMs in fertility and hypogonadism settings |
| hCG (gonadotropin) | Acts like LH at the testes and drives sperm production | Appears in combination protocols, not as a standalone SERM substitute |
Clomiphene: The Agent With the Most Data
Clomiphene is the compound most often studied in men. Its mechanism is indirect: it does not deliver testosterone, it removes part of the brake the pituitary applies when estrogen signalling is high. That is why the published material is careful about who responds, and why the response can be measured in LH, FSH and testosterone rather than guessed.
The side effect profile is documented and worth knowing before any discussion of protocols: reported effects include headache, gynecomastia, visual disturbances, dizziness and mood instability, and the same clinical review notes that serious thromboembolic complications are rare but possible, which is precisely why the risk is discussed before prescribing (Andrology review, pulmonary embolism case report, 2021).
Where the Name Comes From
The condition PCT is aimed at has its own name in the medical literature: anabolic steroid-induced hypogonadism, or ASIH. Published management strategies for ASIH include both testosterone replacement therapy and clomiphene citrate, which is why the two options are often discussed side by side rather than as a single correct answer (Rahnema et al., Fertility and Sterility, 2014).
What the Evidence Shows
The clearest data comes from men treated for hypogonadism and infertility. In one review of that literature, three months of treatment with SERMs produced a statistically significant increase in serum gonadotropins, testosterone, and semen parameters. The same paper is honest about the limits: much of the evidence on tamoxifen in this setting comes from case reports and uncontrolled studies rather than large trials.
There is also a result worth reading twice. In a study of older men, two months of clomiphene raised LH, FSH, and testosterone levels, yet sexual function did not significantly improve despite the higher testosterone. A number on a lab report and a change in how someone feels are not the same measurement.
Who Responds According to the Data
Response is not uniform. Because the mechanism depends on the pituitary being able to answer, clomiphene is less effective at raising testosterone in men whose LH is already elevated before treatment starts. The same review points to men with hypogonadism and LH values at or below 6 IU/mL as the ideal candidates. That is a clinical criterion, and it is one of the reasons a baseline blood panel comes before any protocol rather than after it.
Is PCT Essential, and How Do You Know You Need It
The honest answer is that the literature describes treatment for a diagnosed condition, not a universal step after every course. The population in these studies had hypogonadism, or infertility, or suppressed fertility following exogenous testosterone, and the entry point was laboratory testing. Where that testing shows normal LH and normal testosterone, there is nothing for a SERM to correct.
One more question appears in almost every search on the topic: do SARMs require PCT? The safety reviews on SARMs in healthy adults focus on adverse events, and do not cover recovery protocols. Anything about hormone levels after a suppressive compound is a clinical question, answered with a blood panel rather than with a template copied from a forum.
Tamoxifen: Same Family, Weaker Evidence
Tamoxifen is a SERM with the same pituitary mechanism, and it has been used in men since the 1970s, but its data in this context is thinner. The review quoted above notes that much of the evidence on tamoxifen comes from case reports and uncontrolled studies, which is a different quality of evidence from the controlled work on clomiphene. Two SERMs are not interchangeable just because they share a class.
How Response Is Actually Measured
In the studies above, response was tracked with repeated LH, FSH, and testosterone measurements, and in fertility settings with semen analysis as well. There is no version of PCT where the result can be judged from the mirror or from a training log. If a protocol is being run, the measurement is bloodwork; anything else is guesswork with a confident tone.
hCG Is a Different Tool
hCG is not a SERM and does not belong in the same category. It is a gonadotropin used clinically, and the studies that include it combine it with other agents. In one such protocol, 3000 IU of hCG every other day combined with a SERM, an aromatase inhibitor, or recombinant FSH produced a return of spermatogenesis or improved counts in men who had been suppressed by exogenous testosterone. That is a specific population and a supervised combination, not a single product anyone should swap in for a SERM because it is easier to buy.
What Helps Besides Medication
Sleep is the one non-pharmacological lever with hard data behind it. In a JAMA study, one week of restricting sleep to five hours a night lowered daytime testosterone by 10 to 15 percent in young healthy men (Leproult and Van Cauter, JAMA 2011). That is a change of the same order as the difference between a good and a bad lab result, and it is free.
Beyond that, the reviews cited on this page examine prescription agents. The over-the-counter category sold as PCT support is not covered by them, and no part of this article should be read as a claim that a supplement can replace a SERM.
Five Things People Get Wrong
- Expecting a guaranteed subjective boost. Testosterone rose in the studies; how men felt did not always follow.
- Skipping baseline labs. Without LH and testosterone values, there is no way to tell whether a protocol helped.
- Treating every PCT product as equivalent. The literature covers prescription SERMs and clinical combinations, not the supplements sold under the same name.
- Assuming one protocol fits every cycle. The data comes from specific groups: men with hypogonadism, men with infertility, men recovering fertility after testosterone use.
- Reading marketing as evidence. A large part of what ranks for PCT search terms is dose tables copied between sites with no study behind them.
Questions People Ask
What is PCT in simple terms?
It is the phase after a suppressive course when the aim is to restore the body's own testosterone production, using medicines that raise LH and FSH and confirming the result with bloodwork.
Is PCT essential?
Not as a universal rule. The published evidence describes treatment for a diagnosed condition, with laboratory testing as the entry point rather than a calendar.
How long does PCT last?
In the studies referenced here, treatment periods run from two to three months, with levels measured during and after. Anything shorter is a claim, not a finding.
When should PCT start?
That depends on the compound used and how long it stays active, so it is a clinical decision made with labs, not a fixed number of days copied from a forum.
Clomiphene or tamoxifen?
Both are SERMs that act on the pituitary. Clomiphene has the larger body of data in men with hypogonadism, while the evidence for tamoxifen leans more on case reports and uncontrolled studies.
Do I need bloodwork?
Yes. Every study described here used repeated lab measurements. Without them there is no way to know whether the protocol did anything at all.
What are the side effects of clomiphene?
Reported effects include headache, gynecomastia, visual disturbances, dizziness and mood instability, and rare but serious thromboembolic complications have been described in men taking it.
Do SARMs require a PCT?
The safety reviews on SARMs do not cover recovery protocols. Hormone levels after any suppressive compound are a clinical question, answered with bloodwork rather than a template.
Are over-the-counter PCT supplements enough?
The published evidence is about prescription medicines. Natural products sold as PCT support have not been studied in the same way and should not be presented as replacements.
Can sleep and lifestyle make a difference?
Sleep has the clearest data: one week of five-hour nights lowered testosterone by 10 to 15 percent in young healthy men in a JAMA study.
Important: the medicines discussed here are prescription drugs, and using them to manage hormone levels without supervision carries real risks, including doing the opposite of what you intended. This article summarises published research for information only and is not medical advice. Products sold on this site are intended for research purposes.
If you are planning the recovery phase, start from our post-cycle products, check what is in stock in the full catalog, and read the FAQ for ordering and shipping details.