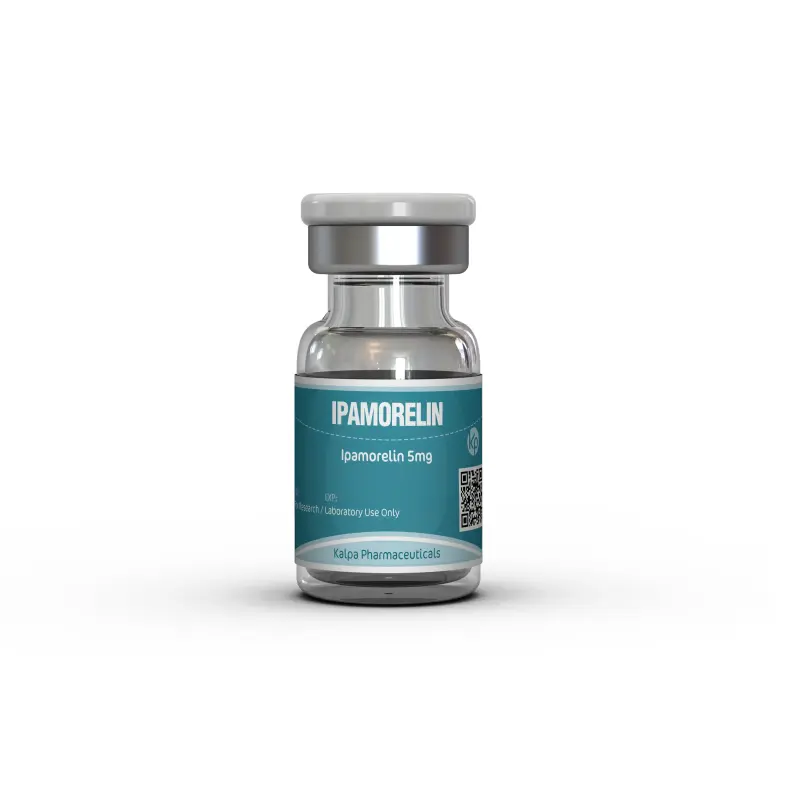
Buy Ipamorelin 5 mg by Kalpa Pharmaceuticals at Best Anabolic Steroids. The pack holds one vial of freeze-dried peptide that is mixed with bacteriostatic water and injected under the skin. Chemically it is a short chain of five amino acids, which is tiny by peptide standards, and it belongs to the group of compounds that prompt the pituitary to release growth hormone rather than supplying the hormone itself.
That distinction decides the whole character of the product. What is released is the user's own growth hormone in a pulse, and the size of the pulse depends on when the injection is given. This is a research material, not a licensed medicine, so the mixing and the timing are entirely the user's work.
Product Overview
Ipamorelin is selective in a way that older ghrelin-mimetic peptides were not. Clinical pharmacokinetic work in healthy volunteers puts the terminal half-life at about two hours, and the same studies describe a growth hormone release that does not come with the pronounced rise in cortisol and prolactin that made earlier compounds in this class uncomfortable for many users. That selectivity is the reason the peptide survives in a market full of short-lived research items.
Two hours of activity sets the practical rules. A single injection produces a short spike, so a schedule with two or three administrations a day is the way a rounded profile is pursued. It also means the injection must land on an empty stomach, because food in the gut blunts the response. The powder dissolves in bacteriostatic water from the same Kali range as Bacteriostatic Water, and it is usually discussed beside the GHRH-based vials Kalpatropin 100 IU and Kalpatropin 200 IU, even though those deliver the finished hormone rather than a stimulus.
Dosage Protocol
There is no approved human dose for athletic use, so the figures below are vendor conventions. They are shown because the arithmetic of a 5 mg vial has to be done correctly in any case.
| Beginner | 200 mcg per injection, two or three times daily. This is the bottom of the range quoted in vendor material |
| Intermediate | 250-300 mcg per injection on the same frequency, which is the usual community schedule |
| Advanced | 300 mcg and above, three times daily. Higher amounts raise the risk of the fluid and joint effects typical of the class |
| Female | No separate female protocol appears in the sources reviewed; the same research amounts are quoted for both sexes |
| Administration | Subcutaneous, on an empty stomach, at least two hours after eating. Typical slots are morning, pre-training and before sleep |
Mixing a 5 mg vial with 2 ml of water gives 2500 mcg per ml, so 10 units on a U-100 syringe is 250 mcg and 8 units is close to 200 mcg. The small injection volumes involved make a U-100 insulin syringe the sensible measuring tool rather than a larger barrel.
Suggested Protocols
The peptide is almost always discussed in pairs, because a ghrelin-receptor agonist and a GHRH-analogue act on two different receptors in the same pituitary cell.
Where a steroid course runs in parallel, the protocols stay separate. If something like Testoxyl Enanthate 400 or Nandroxyl 250 is included, the recovery plan at the end belongs to that compound, and blood work is read with an androgen context in mind.
What to Expect
- Sleep and recovery first. Users most often describe deeper sleep and easier recovery within the first two to three weeks, long before anything changes in the mirror.
- A hormone pulse, not a level. Growth hormone rises and falls within about an hour of the injection, which is why the schedule has several slots rather than one large one.
- Slow body composition change. This is a months-long protocol by nature; a vendor schedule of 12-16 weeks exists because a fortnight of use shows almost nothing.
- The two-hour window is real. Injecting after a meal wastes most of the response, so timing on an empty stomach matters more than adding micrograms.
- Hunger after a shot. The ghrelin route can raise appetite shortly after dosing, which is worth planning around on a cutting diet.
- Banned in competition. The peptide is named in the growth hormone secretagogue class of the prohibited list, with no realistic exemption route.
Side Effects and Management
After the Block and Follow-Up
No SERM is used at the end of an ipamorelin block. The peptide encourages the body's own growth hormone output and leaves the gonadal axis alone, so there is nothing suppressed to restart. What follows a course is a break, not a recovery protocol.
Anyone who has been running an androgen alongside would apply that compound's recovery plan on its own schedule, using the usual restarters from the same line such as Nolvaxyl. The peptide simply stops when the protocol ends.